




















Modernizing Legacy Systems in Healthcare: A Strategic Guide for HealthTech Leaders

 Share -



- 01Legacy Systems in Healthcare: Current Market Statistics and Industry Outlook
- 02Why Modernizing Legacy Systems in Healthcare Is Now a Strategic Priority
- 03Types of Legacy Healthcare IT Systems and Their Modernization Approaches
- 04Key Legacy Healthcare Technology Challenges and How to Overcome Them
- 05Maintaining or Modernizing Healthcare Legacy Systems: How to Make the Right Decision
- 06Modernization in Action: How Leading Healthcare Organizations Are Transforming Legacy Systems
- 07Steps to Modernize Legacy Systems in Healthcare
- 08Healthcare Legacy System Modernization Cost and Major Budget Factors
- 09How to Measure the ROI of Healthcare Legacy System Modernization
- 10Best Practices for Successful Healthcare Legacy Software Modernization
- 11How Appinventiv Can Help Modernize Your Healthcare Legacy Systems
- 12Frequently Asked Questions

Key takeaways:
- Legacy technology still supports critical healthcare workflows, but its security, maintenance, and integration risks continue to grow.
- Modernization should follow a portfolio approach instead of forcing every outdated application through complete replacement.
- Clinical impact, business value, security exposure, and implementation readiness should determine modernization priorities.
- Accurate data migration, standards-based integration, and tested cutover plans are essential for protecting care continuity.
- Modernization costs can range from focused five-figure assessments to multimillion-dollar enterprise transformation programs.
- ROI should measure ownership costs, workforce productivity, system reliability, risk reduction, and digital service delivery.
A hospital rarely continues using old technology by choice. In most cases, the system still performs an essential job. It may process claims, store patient histories, deliver laboratory results, or connect with medical equipment.
Turning it off is not a simple option. Replacing it is not simple either.
Many legacy systems in healthcare sit at the center of interconnected clinical and administrative workflows. One overlooked dependency can interrupt appointments, prescriptions, diagnostic services, or billing. Yet retaining outdated technology creates another set of problems. Maintenance gets harder, cybersecurity gaps widen, and every new integration demands more time and money.
This leaves healthcare leaders with a difficult decision. Which systems should they retain? Which ones can be upgraded? And which have become too costly or risky to keep?
A sensible approach to modernizing legacy systems in healthcare answers these questions before development begins. It protects useful data and proven workflows while gradually removing technical limitations.
This guide explains how organizations can evaluate their systems, select the right modernization approach, estimate costs, plan migration, and measure the results.
Build a modernization roadmap that protects care continuity while creating space for what comes next.
Legacy Systems in Healthcare: Current Market Statistics and Industry Outlook
Legacy modernization for healthcare systems is no longer limited to replacing an old EHR or moving a database to the cloud. Providers and payers are rebuilding the wider technology foundation behind connected care, analytics, automation, cybersecurity, and digital patient services.
Current market activity reflects this change. The global digital transformation in the healthcare market is projected to increase from $98.5 billion in 2026 to $381.5 billion by 2036. This growth shows that healthcare organizations are preparing for operating models that depend on accessible data and connected systems.
Cybersecurity is also influencing investment decisions. Healthcare recorded the highest average data breach cost among industries in 2026 at $6.64 million per incident. Unsupported platforms and poorly connected applications can make prevention, monitoring, and recovery considerably harder.
Regulatory requirements are adding a clear deadline. Affected US payers must implement major API provisions under the CMS Interoperability and Prior Authorization Final Rule by January 2027. Businesses dependent on closed healthcare legacy systems may find these interoperability requirements harder to meet.
The direction of travel is clear. Healthcare businesses are investing in modernization because their future services require secure, available, and interoperable technology. However, market momentum alone does not explain the urgency. The business case becomes clearer when leaders examine how outdated systems affect costs, employees, security, and care delivery.
Why Modernizing Legacy Systems in Healthcare Is Now a Strategic Priority
Outdated technology is no longer a back-office concern. It shapes care delivery, security, operating costs, interoperability, and the pace of digital growth. Modernizing legacy systems in healthcare now belongs on the enterprise agenda.
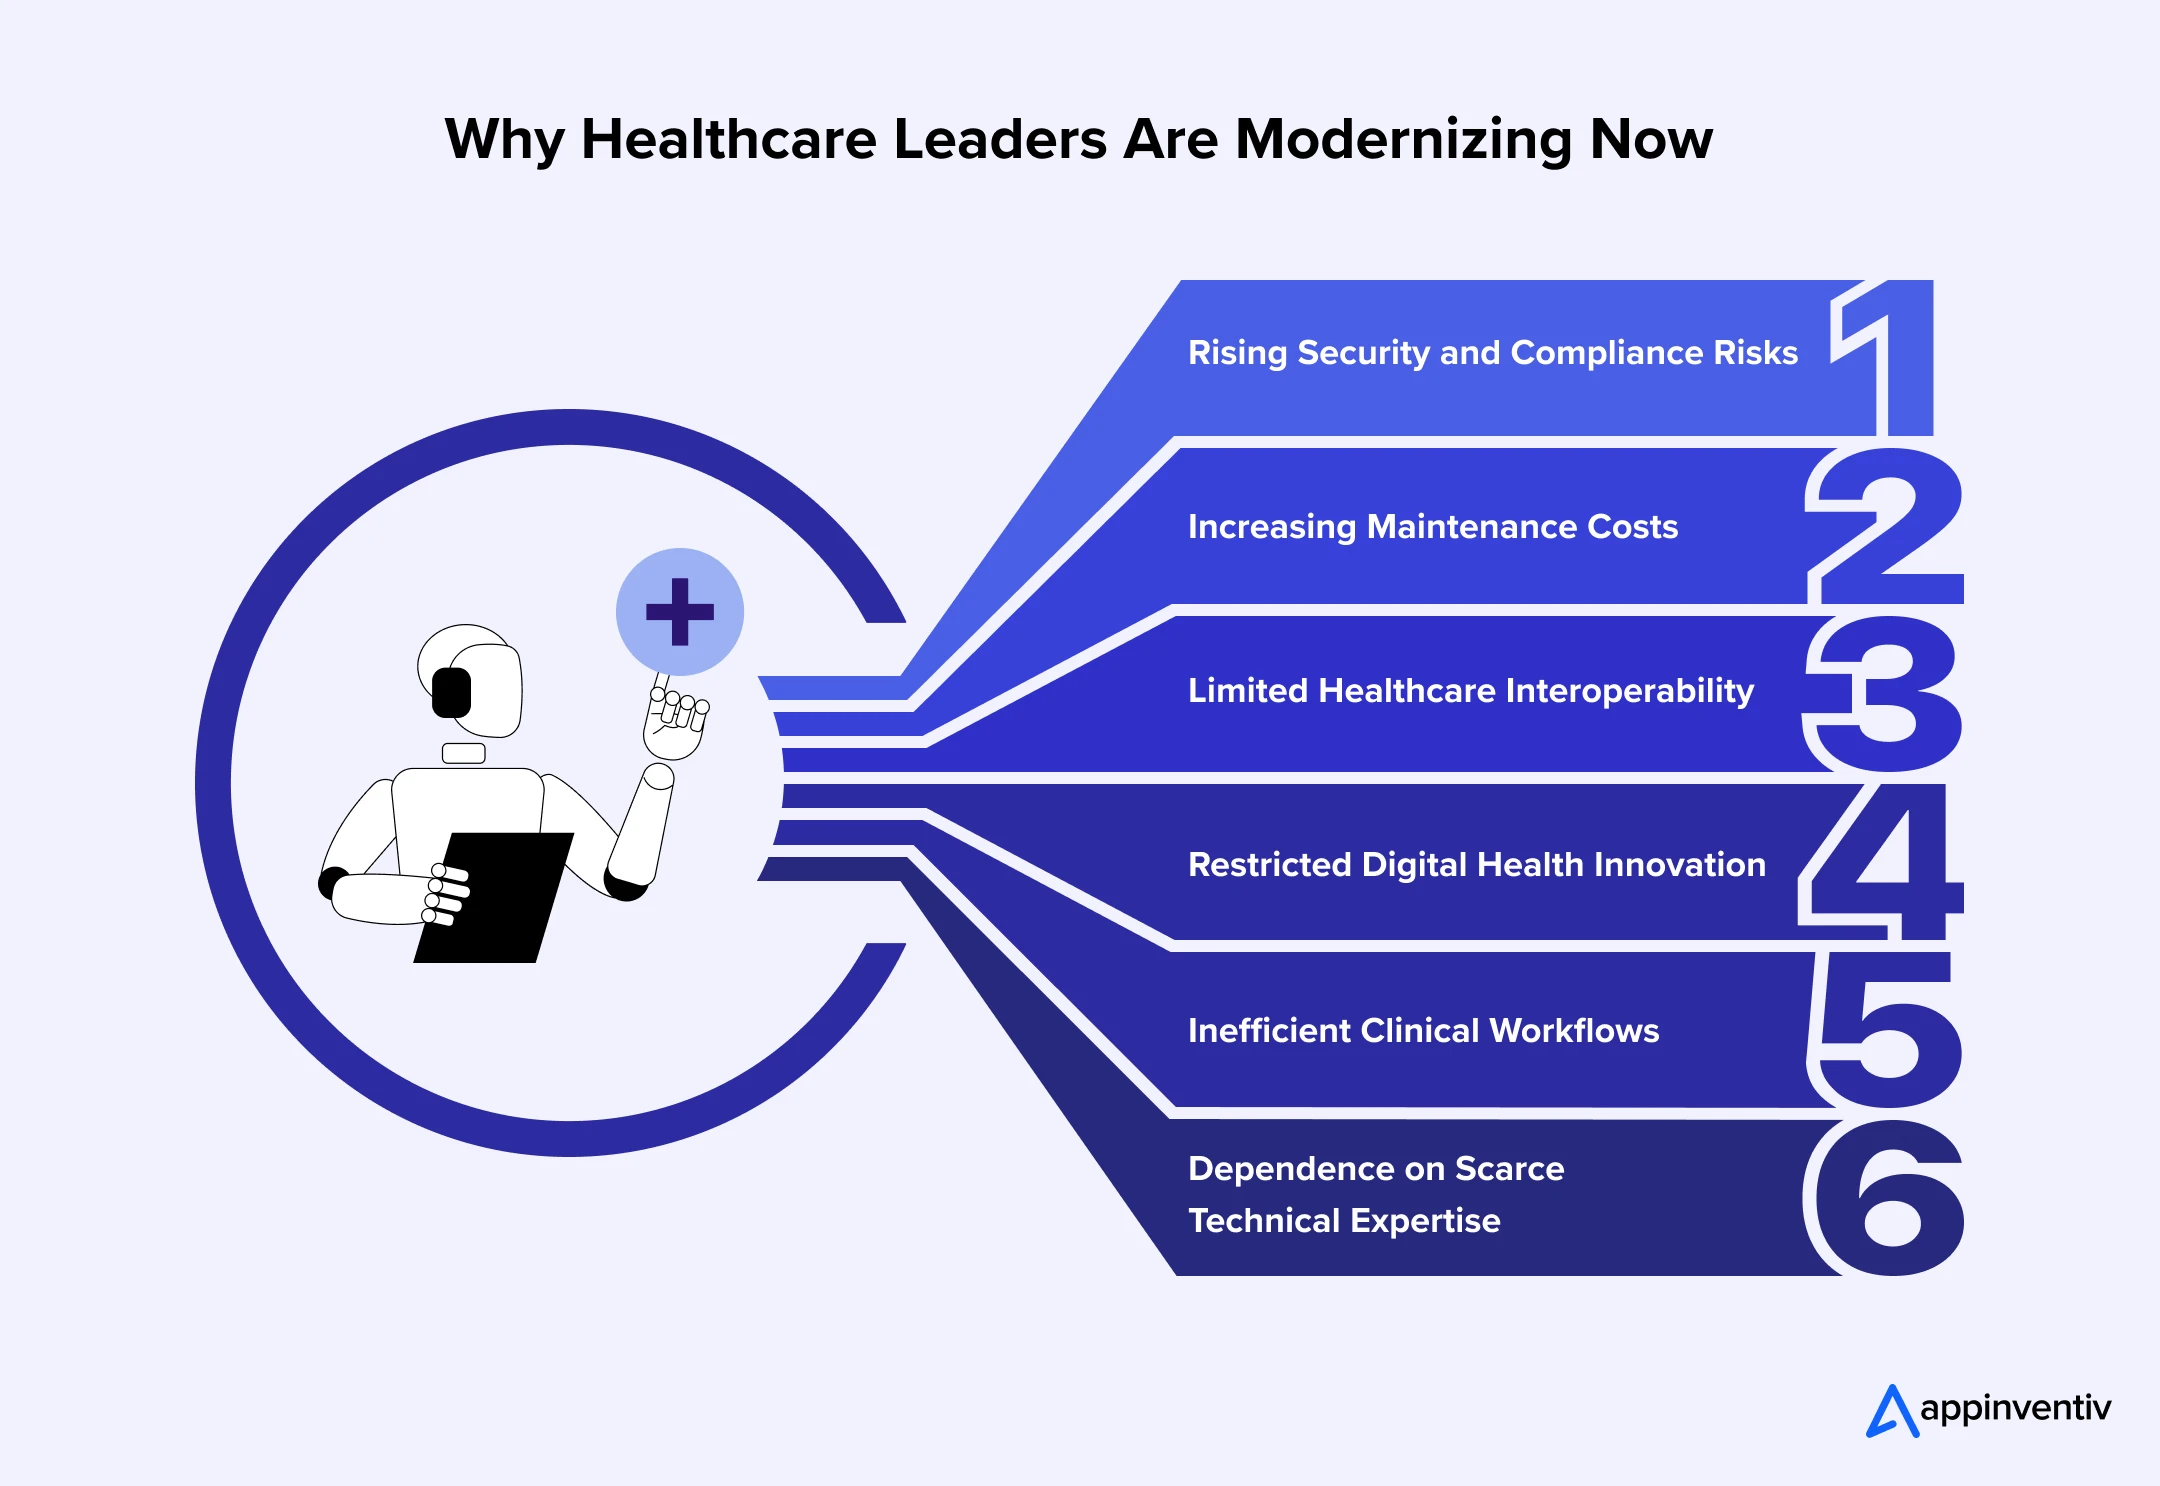
Rising Security and Compliance Risks
Unsupported software may lack current security patches, strong encryption, granular access controls, and detailed audit trails. These limitations create a larger attack surface and make it harder to prove that sensitive information remains protected.
Increasing Maintenance Costs
Older applications often require specialist talent, custom interfaces, extended support, and frequent repairs. That spending keeps the systems operational but does little to improve care or create new business opportunities.
Limited Healthcare Interoperability
Proprietary formats and point-to-point connections make every new data exchange unnecessarily difficult. Connecting EHRs with laboratories, pharmacies, payers, medical devices, and patient applications then becomes a series of expensive one-off projects.
[Also Read: How to Achieve Healthcare Interoperability: A Step-by-Step Implementation Framework for Hospitals and Health Systems]
Restricted Digital Health Innovation
Telehealth, remote monitoring, AI, and patient engagement platforms depend on accessible and well-governed data. When the underlying technology cannot provide that data, promising initiatives often stall during integration.
Inefficient Clinical Workflows
Disconnected systems force employees to switch between screens, re-enter information, and reconcile the same records manually. The additional burden falls on already stretched clinical and administrative teams.
Dependence on Scarce Technical Expertise
Many healthcare legacy systems rely on a small number of professionals who understand obsolete code and undocumented integrations. When these professionals leave, years of operational knowledge may leave with them.
Together, these pressures delay a business decision in its own right. Modernization must still proceed in phases, with clear controls for care continuity and data integrity.
Types of Legacy Healthcare IT Systems and Their Modernization Approaches
The types of legacy healthcare IT systems differ according to specialty, acquisition history, and regulatory environment. A hospital group may inherit dozens of applications through mergers. A diagnostic provider may depend on software tied to equipment that remains clinically useful.
The following categories account for much of the legacy technology footprint.
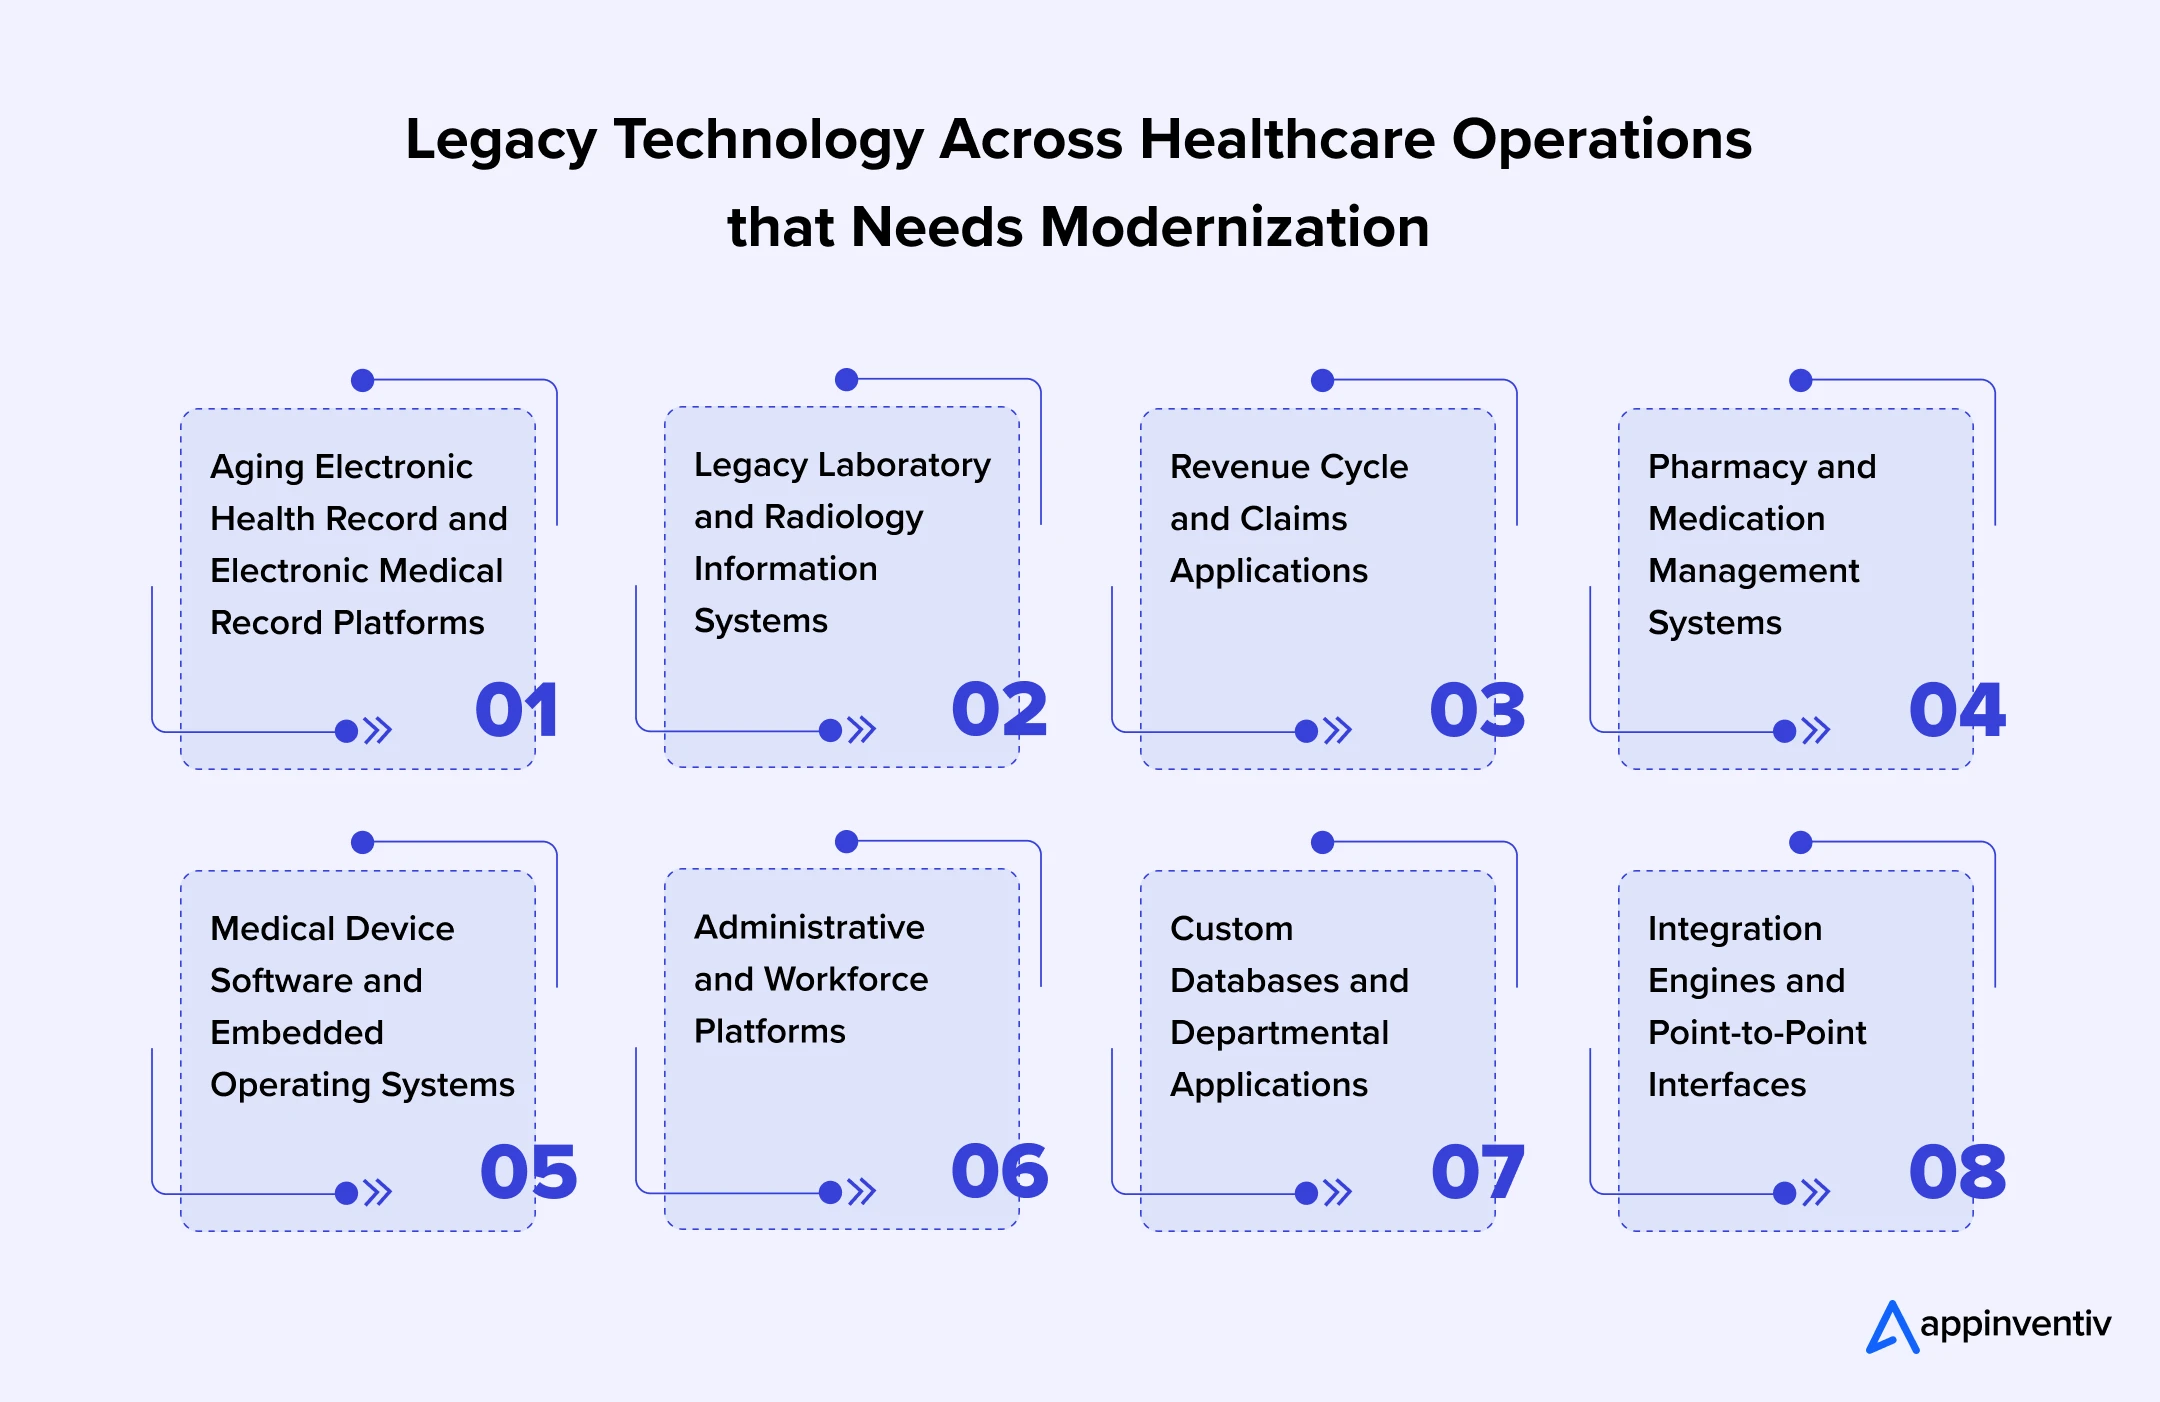
Aging Electronic Health Record and Electronic Medical Record Platforms
Older EHR and EMR products may store essential clinical histories but provide limited interoperability, mobility, and workflow flexibility. Some depend on proprietary databases or outdated client-server architecture.
Other systems remain supported but contain so many customizations that upgrades have become expensive and risky. Healthcare organizations must preserve the clinical information and business rules contained in these platforms during modernization.
Modernization Required: Healthcare providers should move toward modular, API-enabled EHR platforms that support FHIR-based exchange, mobile access, cloud deployment, and scalable integrations. Historical records can be migrated or securely archived, while active clinical workflows should move through controlled implementation phases.
Legacy Laboratory and Radiology Information Systems
Laboratory information systems, radiology information systems, and picture archiving and communication systems manage orders, results, medical images, and reports.
Older products may use inconsistent message formats or depend on aging workstations. Their interfaces can become critical yet poorly documented links within diagnostic workflows.
Modernization Required: These systems require standards-based integration, vendor-neutral storage, and reliable connectivity with EHRs and diagnostic equipment. Healthcare organizations can replatform supported applications, replace obsolete systems, and transfer historical images and reports into secure archives.
Revenue Cycle and Claims Applications
Billing, coding, eligibility, remittance, and claims platforms may contain years of financial records and organization-specific rules. These systems can remain operational long after healthcare providers implement newer front-office applications.
Poor integration can result in repeated data entry, delayed reconciliation, billing errors, and limited visibility into denied claims.
Modernization Required: Revenue cycle modernization should introduce API-based payer connectivity, automated claim validation, real-time eligibility checks, and better financial reporting. Organizations can expose valuable claims logic through APIs before gradually refactoring or replacing outdated modules.
Pharmacy and Medication Management Systems
Legacy pharmacy platforms can support dispensing, formulary rules, medication administration, and inventory management. Their modernization requires particular care.
Incorrect mappings, timing changes, or failed interfaces can introduce medication-related risks. Pharmacy, clinical, and technical teams must therefore validate the system together.
Modernization Required: Providers should prioritize electronic prescribing, real-time EHR integration, standardized medication data, automated interaction checks, and accurate inventory visibility. Every migrated rule and medication workflow requires joint validation by pharmacy, clinical, security, and technical teams.
[Also Read: How to Develop a Pharmacy Management Software – Features, Process, Costs]
Medical Device Software and Embedded Operating Systems
Imaging equipment, bedside devices, laboratory analyzers, and building systems may operate on software that is difficult or impossible to patch.
The equipment itself may remain clinically useful while its embedded operating system becomes a security or connectivity concern. Replacement of medical device software decisions must involve clinical engineering, procurement, cybersecurity, and the device vendor.
Modernization Required: The immediate strategy should include device discovery, network segmentation, access restrictions, continuous monitoring, and secure connectivity gateways. Organizations can then phase device replacement according to vendor support, cybersecurity exposure, clinical value, and capital availability.
Administrative and Workforce Platforms
Scheduling, credentialing, bed management, supply chain, payroll, and workforce applications may not contain complete clinical records. However, their failure can still disrupt healthcare delivery.
These platforms may also contain extensive custom rules that employees treat as institutional knowledge rather than documented system logic.
Modernization Required: Administrative applications should move toward integrated, cloud-ready platforms with configurable workflows and shared operational data. Replatforming or replacement can reduce manual handoffs, improve reporting, and connect staffing and resource decisions with actual service demand.
Custom Databases and Departmental Applications
Clinical and operational teams sometimes create small databases, spreadsheets, or departmental applications to fill functionality gaps.
Over time, these tools can become business-critical without formal ownership, testing, documentation, or recovery processes. They represent some of the least visible healthcare legacy systems.
Modernization Required: Organizations should discover, classify, and document these applications before deciding their future. Unique workflows can be rebuilt as governed platform modules, while duplicated, insecure, or low-value tools should be consolidated or retired.
Integration Engines and Point-to-Point Interfaces
An integration engine may use modern technology while carrying years of undocumented routes and data transformations.
Direct connections using HL7 v2, flat files, database queries, fax workflows, or custom APIs can form a fragile integration web. Changing one endpoint may affect several downstream platforms.
Modernization Required: Healthcare organizations should gradually replace fragile point-to-point connections with governed APIs, reusable integration services, and event-driven exchanges. Centralized monitoring, interface documentation, and standardized data mappings can make future changes faster and safer.
Key Legacy Healthcare Technology Challenges and How to Overcome Them
Clinical, technical, financial, and operational dependencies make healthcare modernization particularly complex. A missed interface or weak migration rule can affect patient records, diagnostics, revenue operations, or regulatory reporting.
The following Legacy systems in healthcare challenges and solutions table connects the major barriers with practical controls.
| Major Challenge | Impact on Healthcare Organizations | How to Overcome It |
|---|---|---|
| Cybersecurity vulnerabilities | Unsupported software, weak access controls, and missing security patches increase the risk of attacks and unauthorized data access. | Isolate vulnerable systems, apply least-privilege access, strengthen monitoring, encrypt data, and prioritize unsupported applications. |
| Poor interoperability | Proprietary formats and rigid interfaces prevent reliable exchanges between EHRs, laboratories, pharmacies, payers, and medical devices. | Implement an integration layer and use suitable standards such as FHIR, HL7, DICOM, and X12. |
| Complex data migration | Inconsistent formats, duplicate records, and missing information can undermine the accuracy of migrated patient data. | Profile, cleanse, map, reconcile, and validate data. Involve clinical owners in approving critical mappings. |
| Risk of operational disruption | Migration errors or extended downtime can interrupt patient registration, documentation, diagnostic services, or billing. | Use phased deployment, parallel testing, cutover rehearsals, downtime procedures, and tested rollback plans. |
| High maintenance costs | Organizations continue spending on aging infrastructure, specialist talent, custom integrations, and extended support. | Calculate the total ownership cost and prioritize systems with the highest combination of cost, risk, and business impact. |
| Regulatory compliance and data privacy | Legacy platforms may lack the consent controls, audit trails, encryption, retention rules, and access governance required under regulations such as HIPAA, GDPR, and applicable regional healthcare laws. Migrating data can create further compliance risks if records lose accuracy, context, or traceability. | Map regulatory requirements before modernization, involve legal and compliance teams, embed privacy-by-design controls, maintain migration audit trails, validate data retention rules, and test access permissions before deployment. |
| Employee resistance | Staff may reject a platform that complicates established workflows or arrives without adequate preparation. | Involve users in workflow design, appoint departmental super-users, and provide scenario-based training. |
| Limited technical expertise | Critical applications may rely on a few professionals familiar with old code, databases, and undocumented interfaces. | Capture system knowledge early, document dependencies, automate testing, and transfer important logic into maintainable platforms. |
| Vendor and technology lock-in | Proprietary formats, restrictive contracts, and closed interfaces make future migration difficult and expensive. | Include data portability, API access, documentation, transition support, and exit provisions in vendor contracts. |
| Unclear dependencies | An apparently minor application may support several downstream clinical or financial processes. | Build a complete inventory of applications, interfaces, data flows, owners, batch jobs, and manual handoffs. |
Replacing old software is only one part of the answer. Leaders must first understand the risks, protect care continuity, and resolve dependencies that could derail the transition. They can then make an informed decision about maintaining, modernizing, replacing, or retiring each system.
Maintaining or Modernizing Healthcare Legacy Systems: How to Make the Right Decision
Not every outdated application needs to be replaced. Some healthcare legacy systems still perform reliably and may remain operational with stronger security and monitoring.
Others create enough clinical, operational, or financial exposure to justify immediate action. System age alone should not determine the decision. Performance, security, interoperability, ownership cost, vendor support, and importance to care provide a stronger basis.
When Maintaining the Existing System Makes Sense
Keeping the system can be practical when it remains stable, secure, supported, and affordable. It may also be the safer short-term choice when replacement would cause more disruption than the existing platform.
Organizations may continue maintaining a platform when:
- The vendor still provides patches and technical support
- The platform meets current security and compliance requirements
- Performance remains stable under existing workloads
- The system supports a limited but essential function
- Required integrations continue operating reliably
- Modernization costs outweigh the immediate business value
- Replacement depends on another planned transformation
- Data can be accessed and recovered without difficulty
Maintenance should not become an indefinite default. The organization must set a review date, monitor emerging risks, and maintain an eventual exit plan.
When Modernization Becomes Necessary
The situation changes when a system limits growth, increases security exposure, or creates unacceptable operational risk. Repeated outages, rising support costs, and an end-of-life notice indicate that continued use may no longer be sustainable.
Organizations should prioritize modernization when:
- Security patches or vendor support are no longer available
- System failures disrupt clinical or administrative operations
- Maintenance requires expensive and scarce expertise
- The platform cannot support necessary integrations
- Employees depend on repetitive manual workarounds
- Data remains inaccessible to analytics and AI platforms
- The system cannot scale with transaction or user growth
- Recovery capabilities fail to meet continuity requirements
- New regulatory or contractual requirements cannot be supported
- Technical limitations delay digital health services
Modernization does not automatically mean replacing the application. The condition of the system, the value of its underlying logic, and the complexity of its dependencies should determine the right route.
Choosing the Right Modernization Approach
| Modernization Approach | When to Choose It | Important Consideration |
|---|---|---|
| Maintain and secure | The system remains stable and supports a limited critical function | Establish compensating controls and a scheduled review date |
| Encapsulate | Valuable functionality must connect with modern applications | Use APIs or middleware without increasing uncontrolled technical debt |
| Rehost | Aging infrastructure creates the primary limitation | Moving the application will not resolve outdated code or workflows |
| Replatform | Selected platform components require improvement | Conduct detailed compatibility and regression testing |
| Refactor | The application provides unique value but remains difficult to modify | Preserve essential business and clinical logic during redevelopment |
| Replace | A modern platform meets requirements better than the existing system | Plan for workflow changes, data migration, integration, and user adoption |
| Retire and archive | The application no longer processes active transactions | Preserve authorized access, retention rules, and audit trails |
Questions to Ask Before Making the Decision
Organizations should use the same assessment framework across their application portfolios. The following questions can reveal whether a platform still deserves further investment:
- Which clinical or business processes depend on the system?
- What would happen if the platform became unavailable?
- Does the vendor still provide patches and support?
- Can the application meet current privacy requirements?
- How much does maintenance and manual workaround activity cost?
- Which systems, devices, and external partners depend on it?
- Can its data be extracted, standardized, and migrated?
- Would an integration layer provide sufficient short-term value?
- Does a suitable replacement already exist?
- Can the organization manage the transition’s operational impact?
- What risks would remain after modernization?
- When should the decision be reviewed again?
The final decision must balance urgency with readiness. A high-risk application may need immediate containment before deeper modernization begins. A stable platform may remain active while the organization addresses more urgent assets.
This portfolio approach directs investment toward systems that create the most risk or restrict the most value. It also keeps healthcare legacy system management focused on clinical continuity rather than unnecessary estate-wide replacement.
Explore our engineering services designed for secure, connected, and scalable healthcare transformation.
Modernization in Action: How Leading Healthcare Organizations Are Transforming Legacy Systems
Healthcare organizations are modernizing legacy technology in different ways. Some are consolidating fragmented EHRs, while others are building modern data layers around valuable historical records. The following legacy systems in healthcare examples demonstrate how providers are improving interoperability, data access, scalability, and care coordination without disrupting essential operations.
AdventHealth: Consolidating Multiple EHR Environments
AdventHealth undertook a large-scale program to move 37 hospitals from different EHR platforms onto one cloud-hosted system. The final hospital completed the transition in February 2024. The initiative gave the health system a more consistent digital foundation across its expanding care network.
Instead of maintaining disconnected clinical platforms, AdventHealth used modernization to standardize workflows and information access. The example shows how enterprise-wide EHR consolidation can reduce fragmentation across hospitals, departments, and regional operations.
Mayo Clinic: Building a Unified Clinical Information Environment
Mayo Clinic replaced separate EHR environments across its major locations with one integrated platform. The program brought clinical, scheduling, registration, and revenue cycle information into a more consistent environment.
This modernization approach helped Mayo Clinic move away from region-specific systems and establish a shared foundation for care delivery. It also demonstrates why large healthcare organizations often treat EHR modernization as an operating-model transformation rather than a routine software upgrade.
University College London Hospitals: Unlocking Legacy Clinical Data
University College London Hospitals deployed the CogStack platform to work with information stored across current and legacy clinical systems. The platform processed more than 18 million records and made unstructured clinical information easier to search and analyze.
UCLH did not need to replace every source system before using the information it contained. Instead, it introduced a modern data and analytics layer around existing records. This approach shows how healthcare organizations can unlock legacy data for research, service improvement, and analytics while a wider modernization program continues.
Kaiser Permanente: Connecting Data Across Care Settings
Kaiser Permanente implemented KP HealthConnect to bring clinical records, appointments, laboratory results, prescriptions, and billing information into a connected digital environment. The platform supports information access across hospitals, medical offices, pharmacies, and laboratories within its network.
The organization’s approach demonstrates the value of replacing fragmented applications with a shared healthcare information environment. It enables professionals to access a more complete patient history when care moves between departments and locations.
These examples show that healthcare modernization does not follow one fixed path. Organizations can consolidate platforms, replace outdated applications, introduce modern data layers, or improve interoperability around systems that still hold business value. The right approach depends on the existing technology estate, clinical risk, data requirements, and long-term operating model.
Steps to Modernize Legacy Systems in Healthcare
Healthcare modernization requires a controlled sequence. The objective is to reduce technical debt without putting patient data, critical workflows, or service continuity at risk.
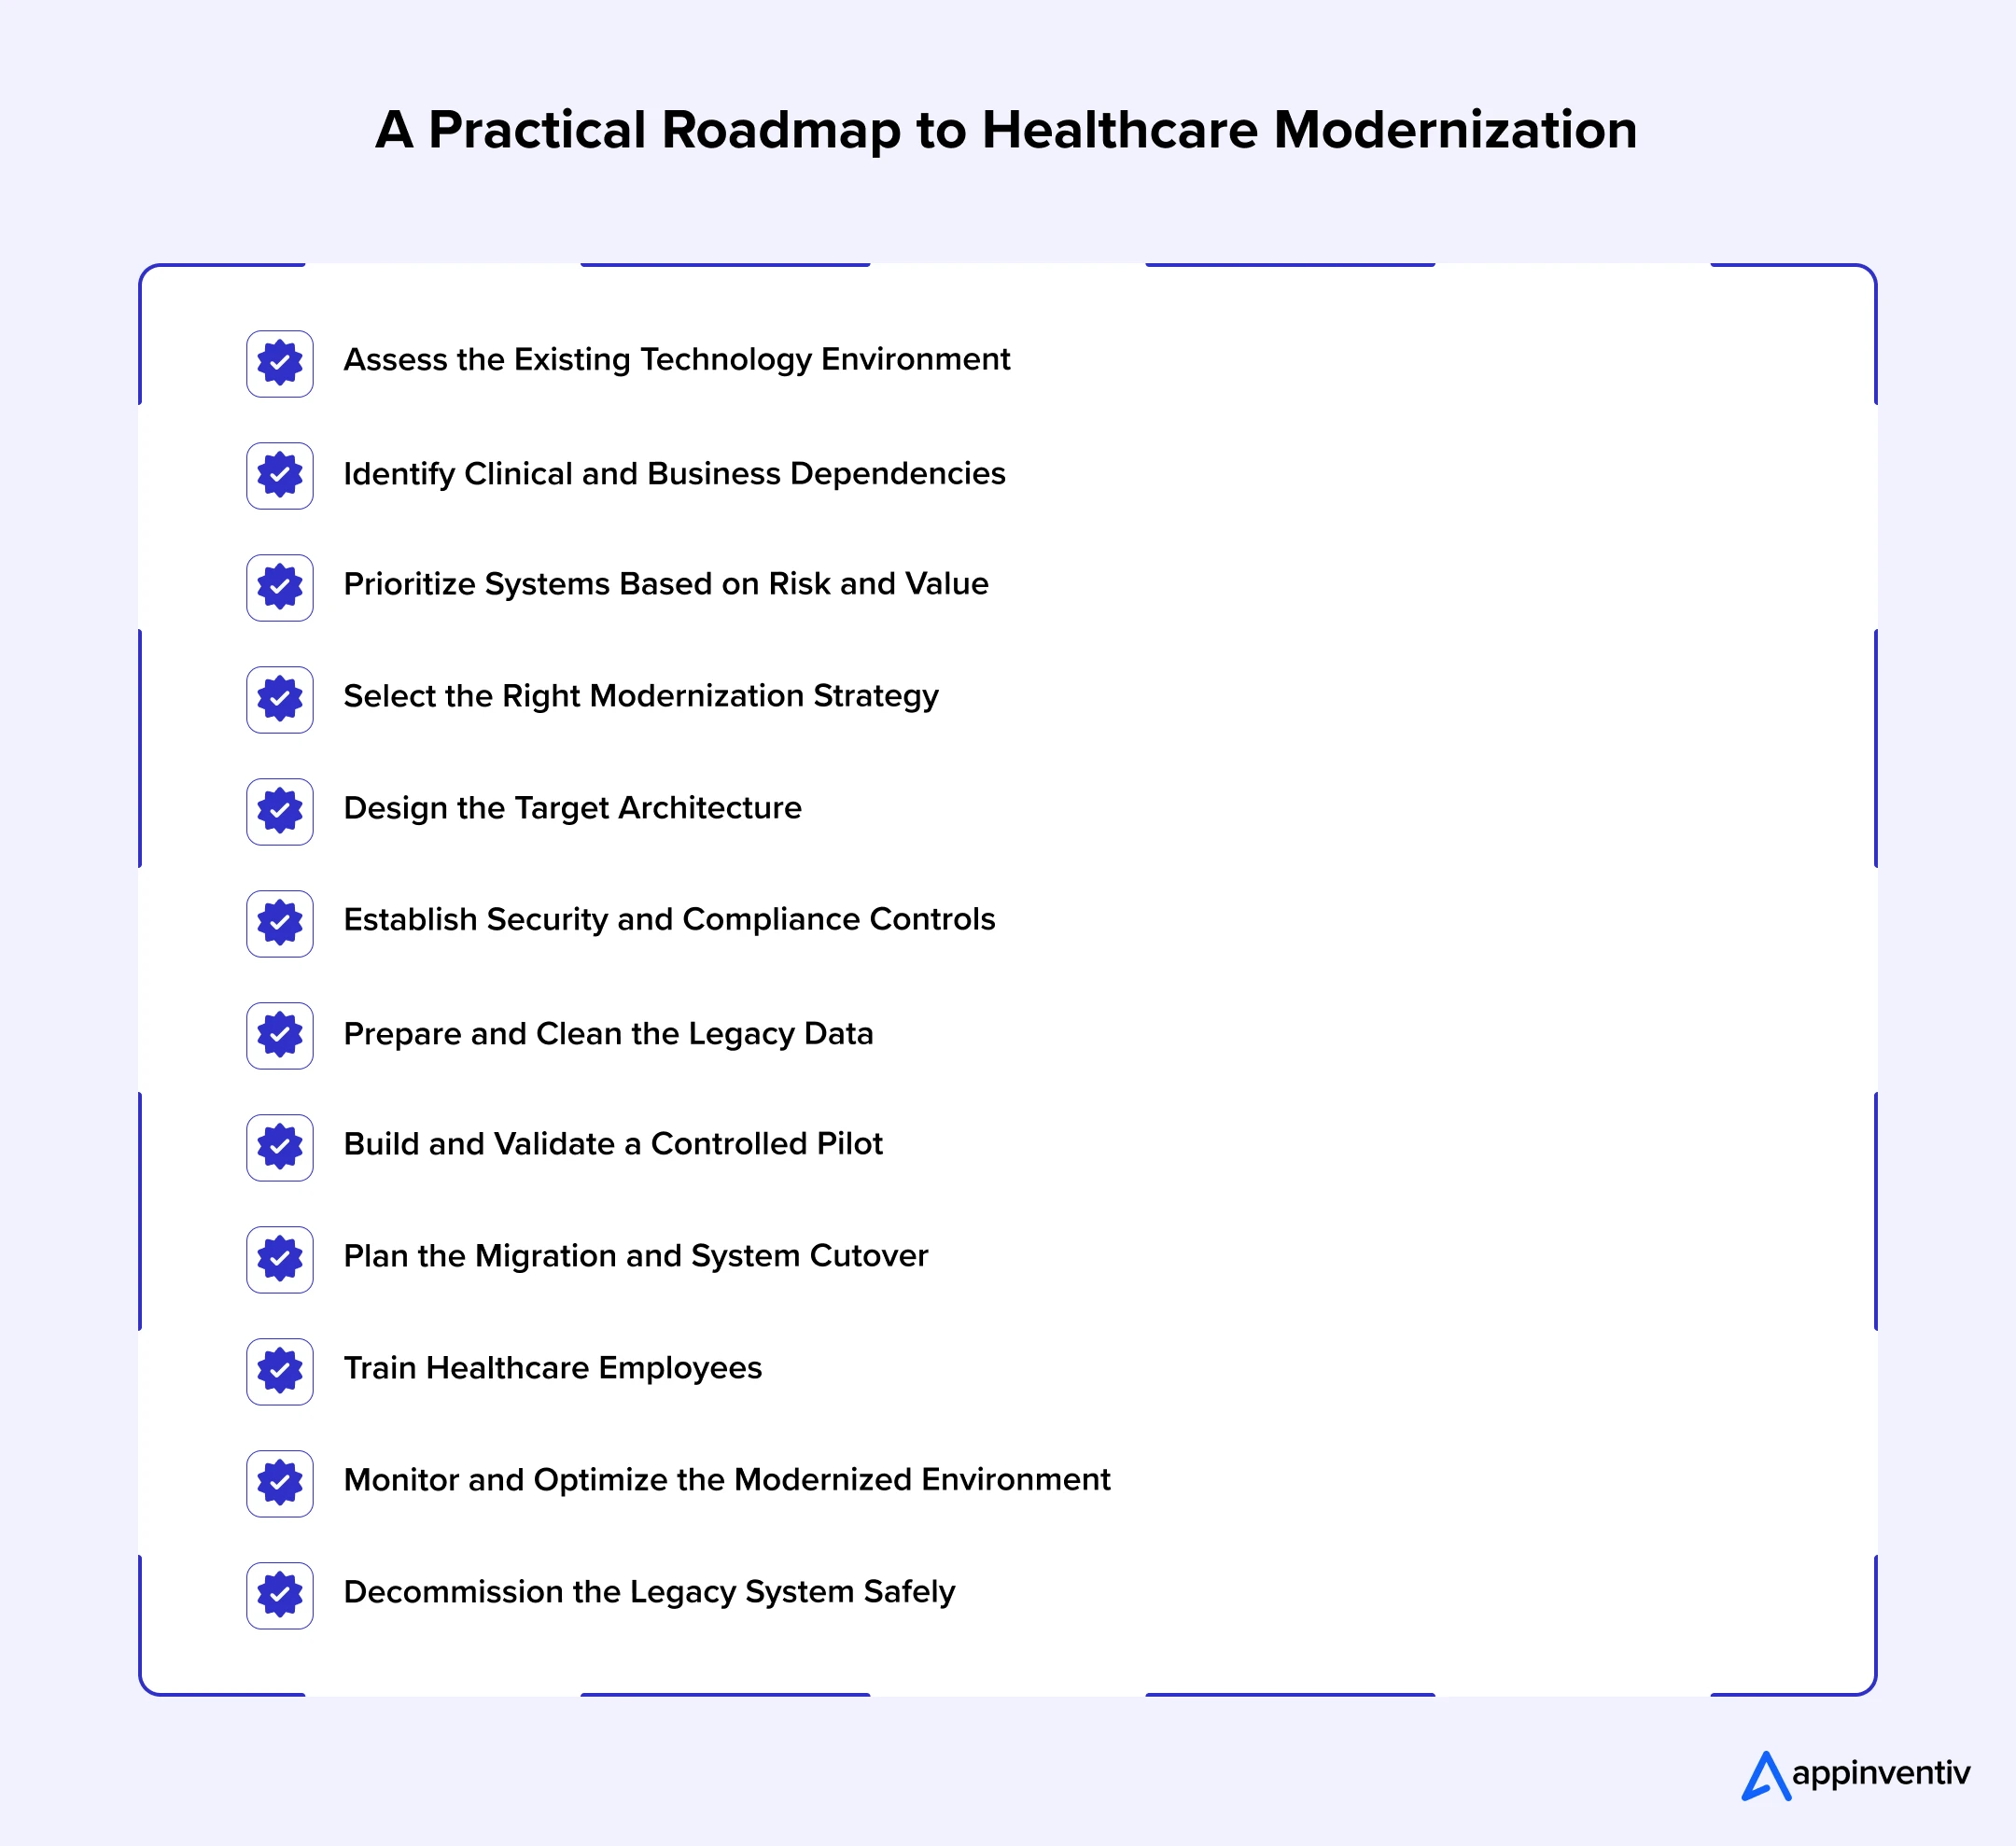
1. Assess the Existing Technology Environment
Build an inventory of applications, databases, infrastructure, medical devices, and third-party tools.
Record the owner, vendor status, hosting model, users, security controls, support costs, and known issues. Unsupported software, repeated outages, and dependence on scarce skills should receive immediate attention.
2. Identify Clinical and Business Dependencies
Trace every application through its clinical, administrative, and financial workflows. A minor-looking platform may feed an EHR, laboratory, billing engine, or regulatory report.
Document APIs, direct interfaces, scheduled files, database connections, manual transfers, and downstream outputs before changing the application.
3. Prioritize Systems Based on Risk and Value
Do not modernize everything simultaneously. Rank applications according to patient impact, cyber exposure, ownership cost, vendor support, operational importance, and strategic value.
Combine urgent projects with several achievable improvements so the program can demonstrate early progress.
4. Select the Right Modernization Strategy
Choose a route based on the application’s condition and future role. Options include maintaining, encapsulating, rehosting, replatforming, refactoring, replacing, and retiring it.
Valuable business logic may justify refactoring or API enablement. A system holding only historical records may belong in a secure archive.
5. Design the Target Architecture
Define how applications, users, data, devices, and external partners will interact within the target environment.
APIs, integration platforms, modular services, and event-based communication can reduce tightly coupled connections. Use FHIR, HL7, DICOM, X12, or another relevant standard according to the actual exchange requirement.
6. Establish Security and Compliance Controls
Involve security, privacy, and compliance teams before development begins. Define data classifications, access roles, encryption, audit controls, retention rules, and incident response responsibilities.
Temporary migration environments, backups, integration accounts, and testing data require the same level of protection as production resources.
7. Prepare and Clean the Legacy Data
Legacy databases commonly contain duplicates, missing fields, outdated codes, inconsistent formats, and unstructured information. Migrating these problems unchanged will weaken the new platform from its first day.
Profile the data, define transformation rules, resolve exceptions, and ask clinical owners to approve mappings that could affect patient care.
8. Build and Validate a Controlled Pilot
Begin with a manageable site, department, application module, or user group. The pilot must be large enough to uncover real workflow and integration problems without exposing the wider organization to unnecessary risk.
Test functionality, security, interoperability, usability, performance, and recovery capabilities against agreed baselines.
9. Plan the Migration and System Cutover
Choose a phased rollout, parallel operation, blue-green deployment, or scheduled full cutover according to the system’s complexity and criticality.
The cutover plan should define:
- Go or no-go criteria
- Migration responsibilities
- Downtime procedures
- Rollback conditions
- Communication protocols
- Issue escalation routes
- Command-center support
- Post-launch monitoring
Run at least one complete rehearsal using production-like data volumes and realistic operating conditions. A plan that works only on paper is not a dependable cutover plan.
10. Train Healthcare Employees
Training must reflect the work employees actually perform. Clinicians, administrators, billing teams, and technical professionals require different scenarios and support resources.
Prepare departmental super-users early. Support them with practice environments, quick-reference guides, and on-site assistance during launch.
11. Monitor and Optimize the Modernized Environment
After launch, monitor system performance, interface success, data quality, user adoption, security events, and workflow efficiency. Compare the results with the original modernization goals.
A new workaround may indicate a training issue. However, it could also expose a genuine design or functionality gap.
12. Decommission the Legacy System Safely
Healthcare legacy system modernization remains incomplete while redundant applications and infrastructure continue operating. Duplicate platforms preserve unnecessary costs and cybersecurity exposure while increasing the risk of inconsistent records.
Before retirement, confirm:
- Completion of data reconciliation
- Availability of historical records
- Compliance with retention requirements
- Resolution of active legal holds
- Closure of downstream interfaces
- Removal of user and service accounts
- Termination of unnecessary vendor contracts
- Secure disposal of hardware and stored information
A secure archive can preserve historical records without keeping the complete legacy application operational. This is also where replacing legacy systems in healthcare produces measurable savings instead of creating another technology layer.
Healthcare Legacy System Modernization Cost and Major Budget Factors
Healthcare legacy system modernization cost depends on the number of systems, clinical criticality, data condition, integrations, security requirements, and rollout scale.
A focused application project may require a comparatively limited budget. A multi-site EHR or enterprise platform transformation can become a multi-year investment.
The following estimates can support initial planning:
| Modernization Scope | Typical Inclusions | Estimated Cost |
|---|---|---|
| Legacy system assessment | Application audit, dependency mapping, risk analysis, and roadmap | $20,000–$50,000 |
| Focused rehosting project | Infrastructure migration, configuration, testing, and deployment | $40,000–$100,000 |
| Application replatforming | Platform upgrades, database changes, integrations, and security improvements | $75,000–$200,000 |
| Legacy application refactoring | Code restructuring, architecture redesign, API development, and testing | $100,000–$400,000 |
| Complete custom system replacement | Development, migration, integration, validation, training, and deployment | $200,000–$500,000+ |
| Enterprise-wide modernization | Multiple systems, facilities, data repositories, devices, and workflows | $500,000–several million |
These ranges are directional and should not be treated as fixed quotations. Undocumented interfaces, poor data quality, medical device dependencies, and specialized compliance requirements can materially affect the investment.
Replacing legacy systems in healthcare usually becomes more expensive when organizations begin discovery late. A dedicated assessment phase can provide a more reliable estimate before development starts.
How to Measure the ROI of Healthcare Legacy System Modernization
Measuring ROI helps distinguish a business transformation from a basic technology refresh. Healthcare organizations should evaluate financial, operational, clinical, and strategic returns.
The process should begin before implementation and continue after each modernization phase.
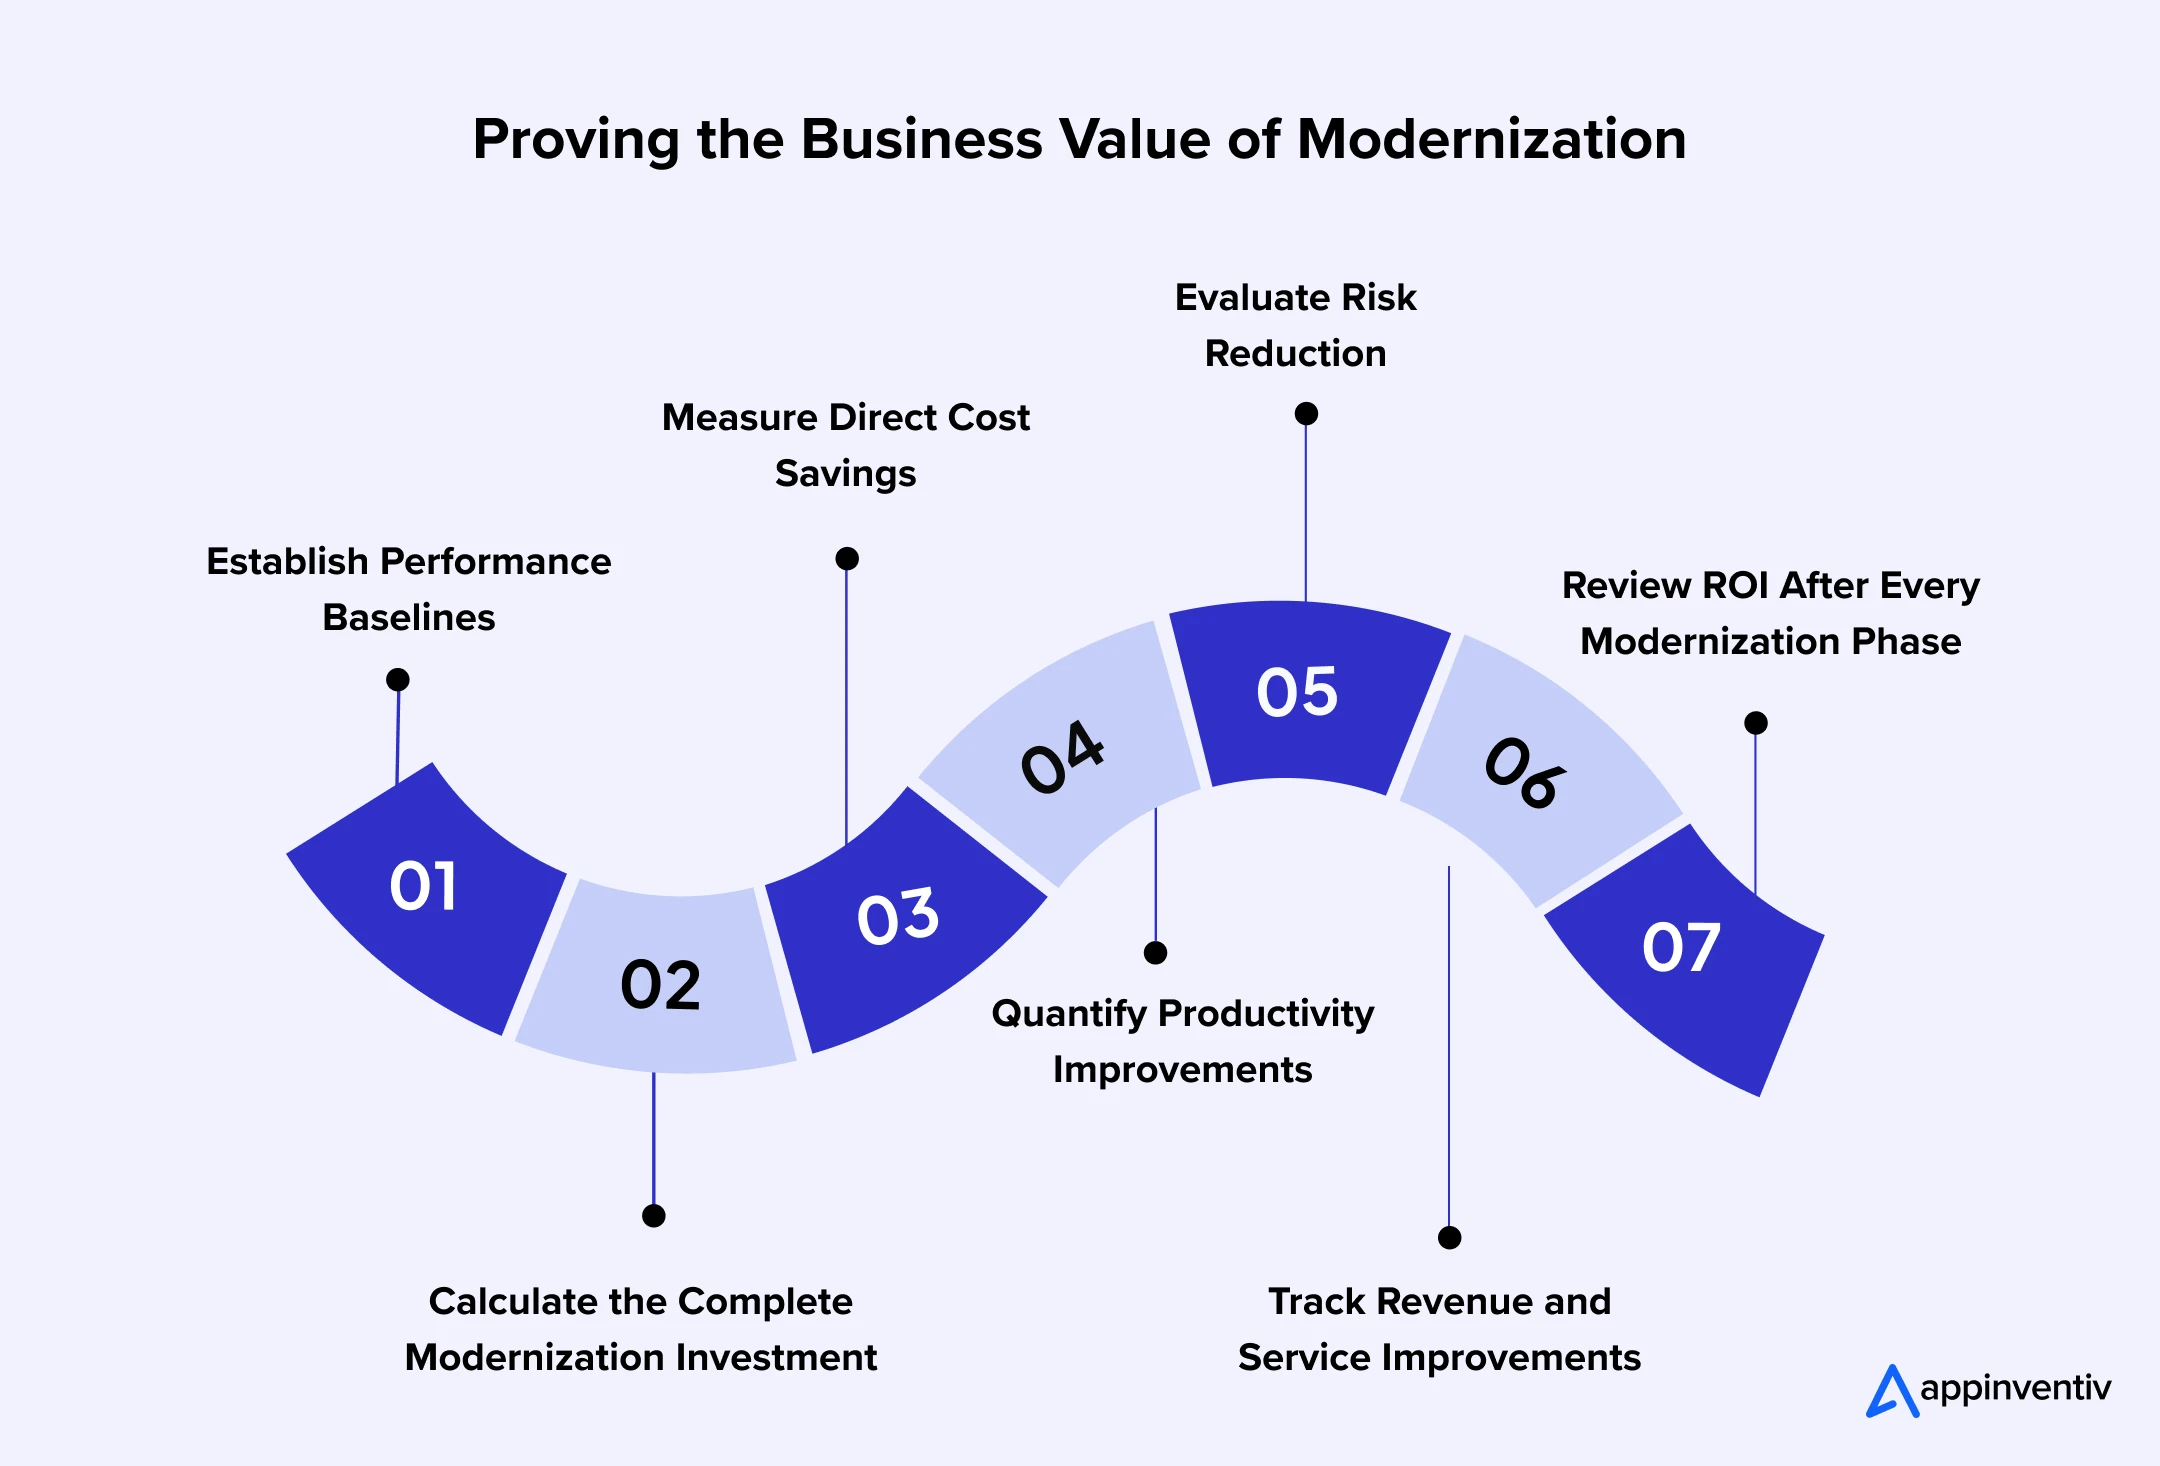
Establish Performance Baselines
Record the current cost, performance, and risk of the legacy environment. Maintenance expenditure, downtime, task completion time, interface failures, security findings, and support demand provide a measurable starting point.
Without reliable baseline figures, teams cannot demonstrate whether modernization has produced genuine improvements.
Calculate the Complete Modernization Investment
Include discovery, development, infrastructure, licenses, data migration, integration, testing, training, security, and post-launch support.
Development cost alone will understate the total investment and produce a misleading ROI calculation.
Measure Direct Cost Savings
Calculate savings from retired hardware, data centers, duplicate applications, extended vendor support, and specialist resources.
Organizations can also include the value of eliminated manual work. However, they should document the assumptions behind these calculations.
Quantify Productivity Improvements
Compare the time required to complete high-volume processes before and after modernization.
Suitable workflows may include patient registration, clinical record retrieval, claims processing, result delivery, appointment management, and record reconciliation.
Evaluate Risk Reduction
Track unsupported assets, critical vulnerabilities, unplanned outages, excessive access permissions, and unresolved audit findings.
Risk reduction may not generate immediate revenue. However, it protects the organization against avoidable operational, regulatory, and financial losses.
Track Revenue and Service Improvements
Determine whether modernization has accelerated claims, reduced billing errors, improved patient access, or supported new digital healthcare services.
These outcomes connect the technology investment with revenue growth, cash flow, patient acquisition, and market expansion.
Review ROI After Every Modernization Phase
Compare actual results with the original targets after every release. Use this evidence to correct underperforming areas and select the next group of healthcare legacy systems for modernization.
A simple financial calculation can be used:
ROI = [(Total Financial Benefits − Modernization Investment) ÷ Modernization Investment] × 100
This percentage should be reviewed alongside operational, clinical, security, and experience metrics. Some of the most valuable benefits may not produce immediate financial returns.
Turn a complex technology estate into clear, risk-backed modernization decisions.
Best Practices for Successful Healthcare Legacy Software Modernization
Healthcare legacy software modernization involves technology, clinical operations, data, security, compliance, and workforce planning. The following practices can keep the program grounded in real healthcare requirements.
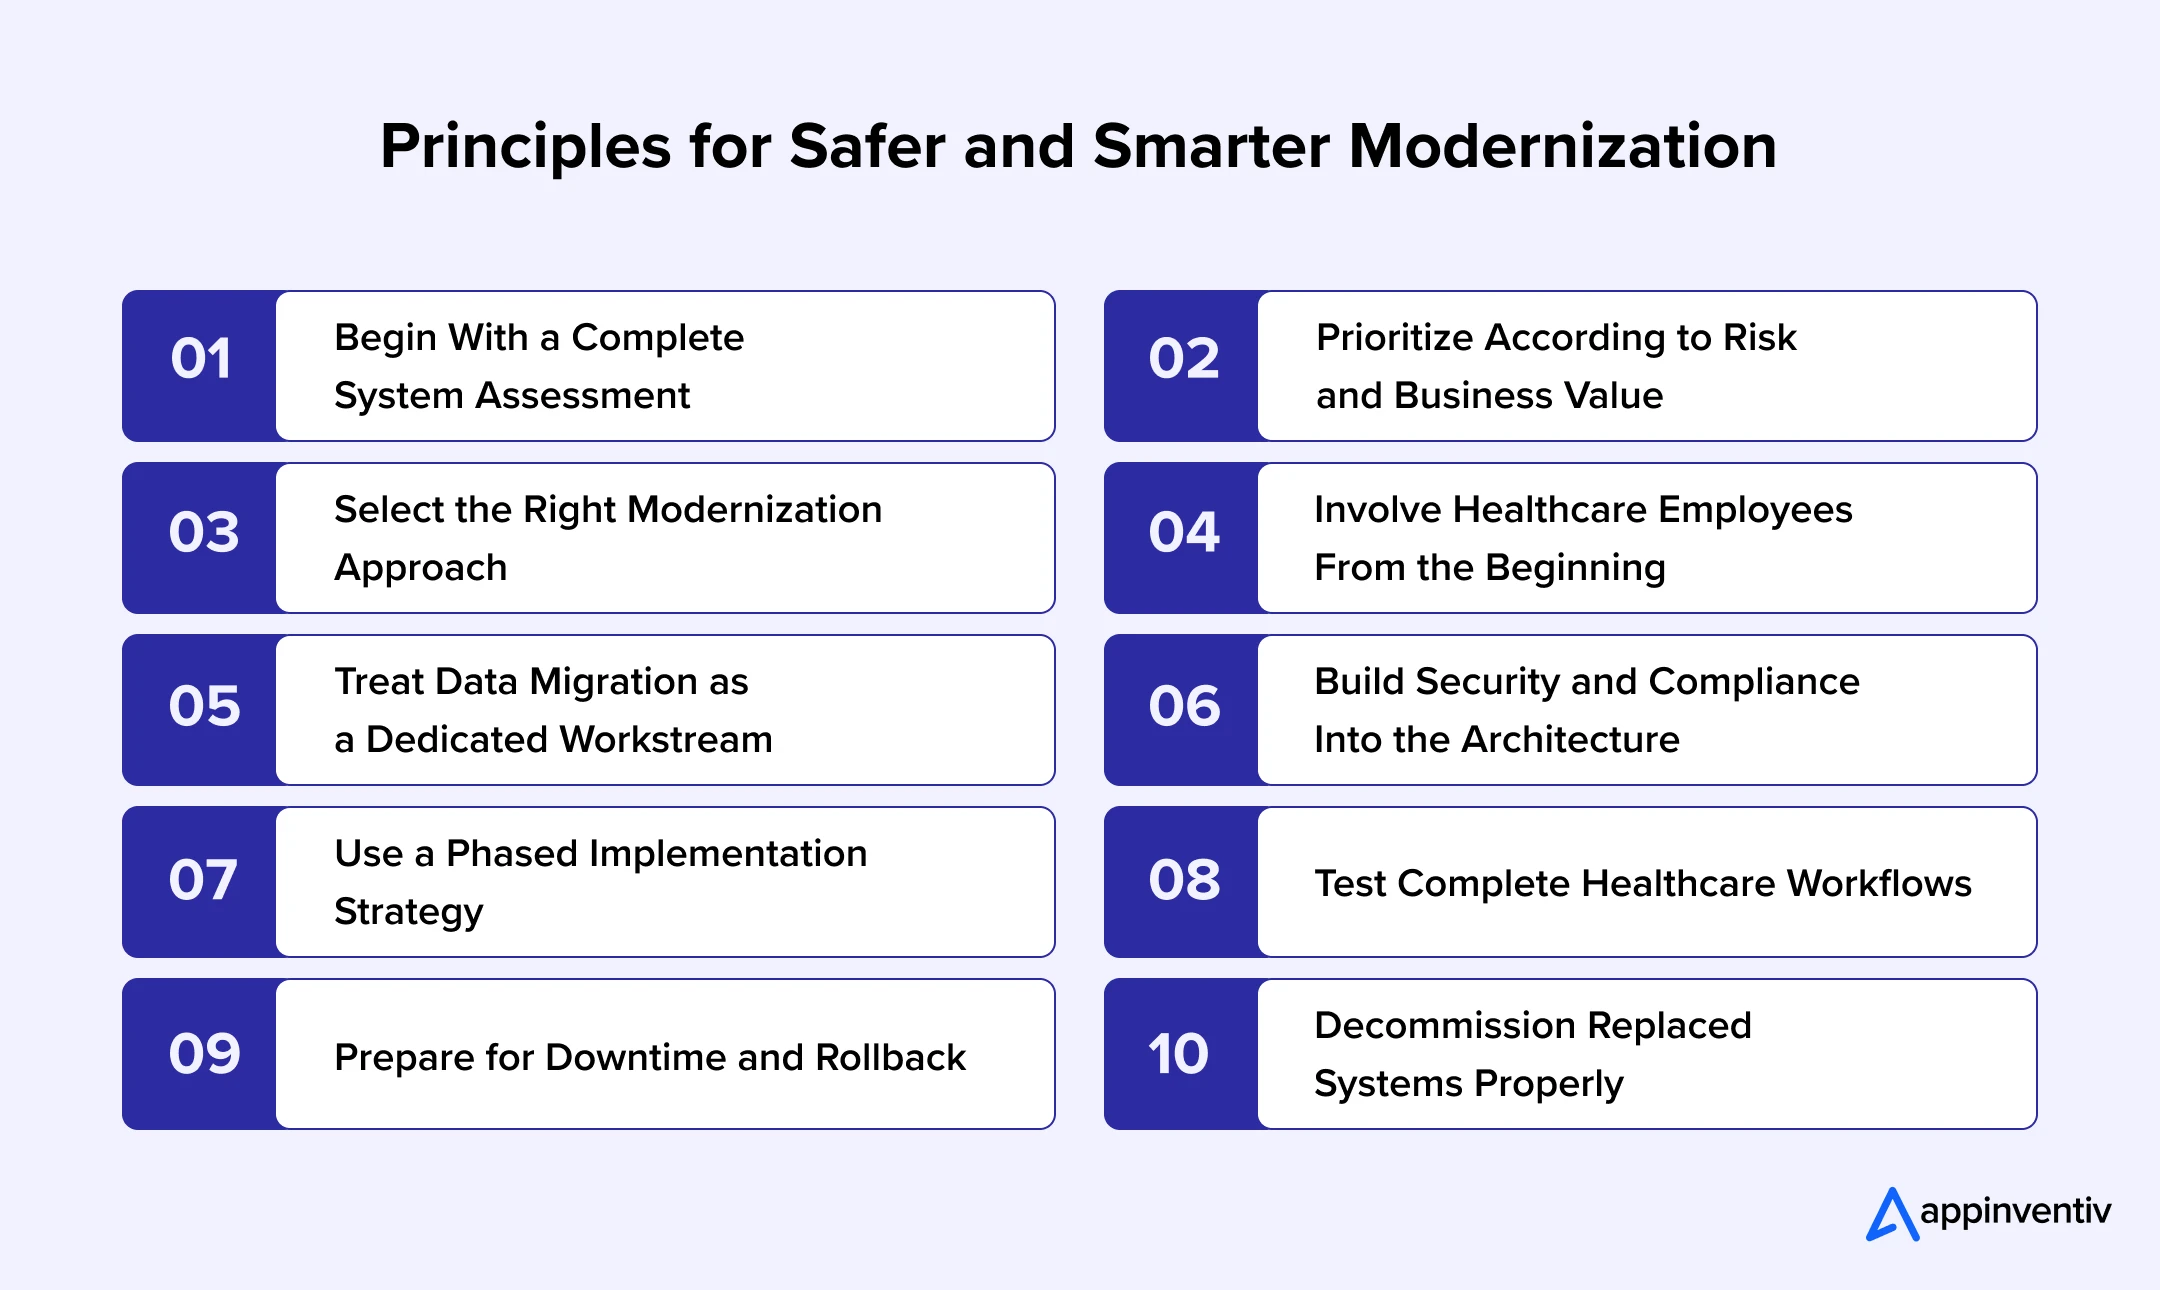
Begin With a Complete System Assessment
Assess applications, databases, interfaces, infrastructure, and manual dependencies together. Identify the owner, users, vendor status, security gaps, support costs, and operational role of each asset.
Without this information, a modernization roadmap becomes a collection of assumptions rather than an informed transformation plan.
Prioritize According to Risk and Business Value
Prioritize systems according to patient impact, security exposure, ownership cost, performance, and strategic importance.
An unsupported application containing sensitive data deserves more immediate attention than a stable departmental tool. Balance complex, high-risk projects with initiatives capable of producing early value.
Select the Right Modernization Approach
Not every application requires a complete rebuild. Maintain, rehost, replatform, refactor, encapsulate, replace, or retire it according to the asset’s condition and future value.
The right modernization approach prevents unnecessary redevelopment while limiting clinical and operational disruption.
Involve Healthcare Employees From the Beginning
Include clinicians, administrators, and support teams in requirements gathering, workflow design, testing, and training.
These employees understand the exceptions and informal processes that rarely appear in system documentation. Early involvement also gives users a reason to trust the change rather than work around it.
Treat Data Migration as a Dedicated Workstream
Give data migration its own team, budget, schedule, and acceptance criteria. Profile, clean, map, reconcile, and test records before transferring them.
Clinical and business owners must approve critical transformations to ensure that the information retains its original meaning.
Build Security and Compliance Into the Architecture
Establish security, privacy, and compliance requirements during planning rather than after development.
The architecture should address access controls, encryption, auditability, data retention, backup protection, and incident response. This approach prevents late redesign and reveals weak assumptions early.
Use a Phased Implementation Strategy
A phased rollout gives the organization a controlled environment for testing the solution. Begin with one location, department, or user group before expanding the deployment.
Lessons from each phase should improve subsequent releases. Workflow, data, and integration problems are easier to resolve before they spread across the healthcare network.
Test Complete Healthcare Workflows
Test complete patient, clinical, administrative, and financial journeys instead of isolated technical functions.
Include routine processes, exceptions, integration failures, peak workloads, and downtime conditions. Clinical professionals should approve every workflow capable of affecting patient safety.
Prepare for Downtime and Rollback
Every deployment requires usable downtime procedures and a tested rollback plan.
Define cutover ownership, escalation routes, communication protocols, recovery targets, and go or no-go criteria. Rehearse them under realistic conditions before the live transition.
Decommission Replaced Systems Properly
Do not leave the old platform operational simply because employees remain familiar with it.
Confirm data reconciliation, historical access, retention compliance, interface closure, account removal, and contract termination before retirement. Proper decommissioning eliminates duplicate expenses and closes avoidable security gaps.
Applied consistently, these practices make legacy system modernization for healthcare safer and easier to govern. They also keep modernizing legacy systems in healthcare connected with measurable business outcomes rather than isolated technology improvements.
How Appinventiv Can Help Modernize Your Healthcare Legacy Systems
Replacing an outdated application is rarely the hardest part of healthcare modernization. The real work lies in understanding clinical workflows, system dependencies, data, security exposure, and compliance obligations.
Appinventiv helps healthcare organizations turn that complexity into a phased modernization roadmap. Our teams assess applications, infrastructure, databases, integrations, and operational bottlenecks before recommending a suitable transformation approach.
Depending on the asset, that approach may include rehosting, replatforming, refactoring, API enablement, complete replacement, or secure retirement.
As a healthcare software development company, our experts build scalable platforms and connect EHRs, laboratories, pharmacies, medical devices, payer systems, and patient applications. The architecture uses healthcare standards suited to the required exchange and the organization’s operating model.
We also plan data migration around accuracy, availability, and clinical meaning. Data profiling, cleansing, mapping, reconciliation, validation, controlled access, and compliant archival form part of the same delivery process.
From discovery and architecture to testing, rollout, and optimization, our legacy application modernization services support the complete transformation journey while protecting data integrity, care continuity, and long-term technology investments.
Frequently Asked Questions
Q. What are the latest healthcare legacy system modernization strategies?
A. Current strategies allow organizations to improve legacy healthcare systems without automatically replacing the entire technology estate. The appropriate approach for modernizing legacy systems in healthcare depends on the application’s condition, business value, security exposure, and future role.
Healthcare legacy software modernization strategies include:
- Rehosting applications on modern infrastructure
- Replatforming databases and runtime environments
- Refactoring applications into modular components
- Encapsulating existing functions through APIs
- Replacing obsolete platforms with custom solutions
- Moving historical information into secure archives
- Adopting cloud-native and event-driven architecture
- Introducing FHIR-based interoperability where appropriate
Q. How do healthcare providers migrate data from legacy systems to modern platforms?
A. Healthcare providers use a controlled migration process that preserves record accuracy, clinical meaning, security, and regulatory compliance. The process begins with data assessment and continues through post-migration validation.
The major steps include:
- Inventorying available records and data sources
- Profiling data quality and identifying inconsistencies
- Removing duplicates and correcting invalid information
- Mapping legacy fields to the target data model
- Standardizing formats, codes, units, and identifiers
- Running test migrations with representative records
- Reconciling migrated data with the source system
- Obtaining clinical and business approval
- Archiving information that does not require active migration
Q. How can healthcare legacy systems be prepared for software modernization?
A. Preparation begins with understanding how each platform supports clinical, administrative, and financial operations. Organizations must identify hidden dependencies before changing the application or moving its data.
This groundwork makes legacy system modernization for healthcare more predictable. Healthcare organizations should:
- Document applications, infrastructure, and integrations
- Identify system owners and user groups
- Review vendor support and technology obsolescence
- Assess security, privacy, and compliance risks
- Map clinical and operational dependencies
- Evaluate data quality and migration readiness
- Define measurable modernization objectives
- Select the appropriate transformation approach
- Prepare downtime, recovery, and rollback procedures
Q. How much does healthcare legacy system modernization cost?
A. Healthcare legacy system modernization cost varies according to the application scope, technical complexity, data volume, integrations, security requirements, and number of deployment locations.
A focused assessment or rehosting project costs considerably less than replacing a multi-site clinical platform. The final budget may include:
- Application and infrastructure assessment
- Architecture and experience redesign
- Custom development or platform configuration
- Cloud infrastructure and software licensing
- API and third-party integration
- Data cleansing, migration, and validation
- Security and compliance implementation
- Quality assurance and clinical testing
- Employee training and change management
- Deployment and post-launch support
Q. How can healthcare organizations maintain care continuity during modernization?
A. Healthcare organizations can protect care continuity by modernizing legacy healthcare systems in controlled phases and preparing fallback processes for critical workflows.
Every cutover decision should account for its potential impact on patients, clinicians, and connected departments. Organizations should establish:
- Phased or parallel deployment plans
- Clearly defined go or no-go criteria
- Tested downtime and recovery procedures
- Data reconciliation checkpoints
- Rollback conditions and responsibilities
- Clinical escalation channels
- Real-time command-center support
- Post-deployment monitoring
- Role-based employee training
- Backup access to essential patient information


Fast 2-minute response, fully NDA-protected.

Sleep Tracker App Development: Features, Wearable Integration, AI, and Compliance
Key takeaways: Sleep tracking presents opportunities across consumer wellness, fitness, healthcare, employee wellness, senior care, and infant-care markets. Successful products combine actionable insights, wearable connectivity, user-friendly reports, privacy controls, and clearly differentiated experiences. HealthKit, Health Connect, and direct device APIs provide different data depths, costs, limitations, and maintenance requirements. AI supports sleep-stage estimation and personalization,…

Diet and Nutrition App Development: Process, Features, Cost, and Technology Stack
Key Takeaways Diet and nutrition tracking app development goes past basic calorie counters with verified food databases, custom meal schedules, AI tools, wearable device links, and corporate manager tools. Structure database models around raw food items, serving portions, nutrient facts, recipes, software links, and regional diet rules. Pair computer vision models, recommendation algorithms, language engines,…

eCOA Software Development Guide: Enterprise Architecture, Tech Stack, Development Process, and Cost
Key takeaways: Build an enterprise eCOA platform using cloud servers, AI tools, and compliant system design. Map the full eCOA development process, from trial workflow analysis to live system maintenance. Connect your platform with EDC, CTMS, eConsent, HL7 FHIR, and wearables to simplify trial data sharing. Compare custom software against off-the-shelf platforms to make smart…



